


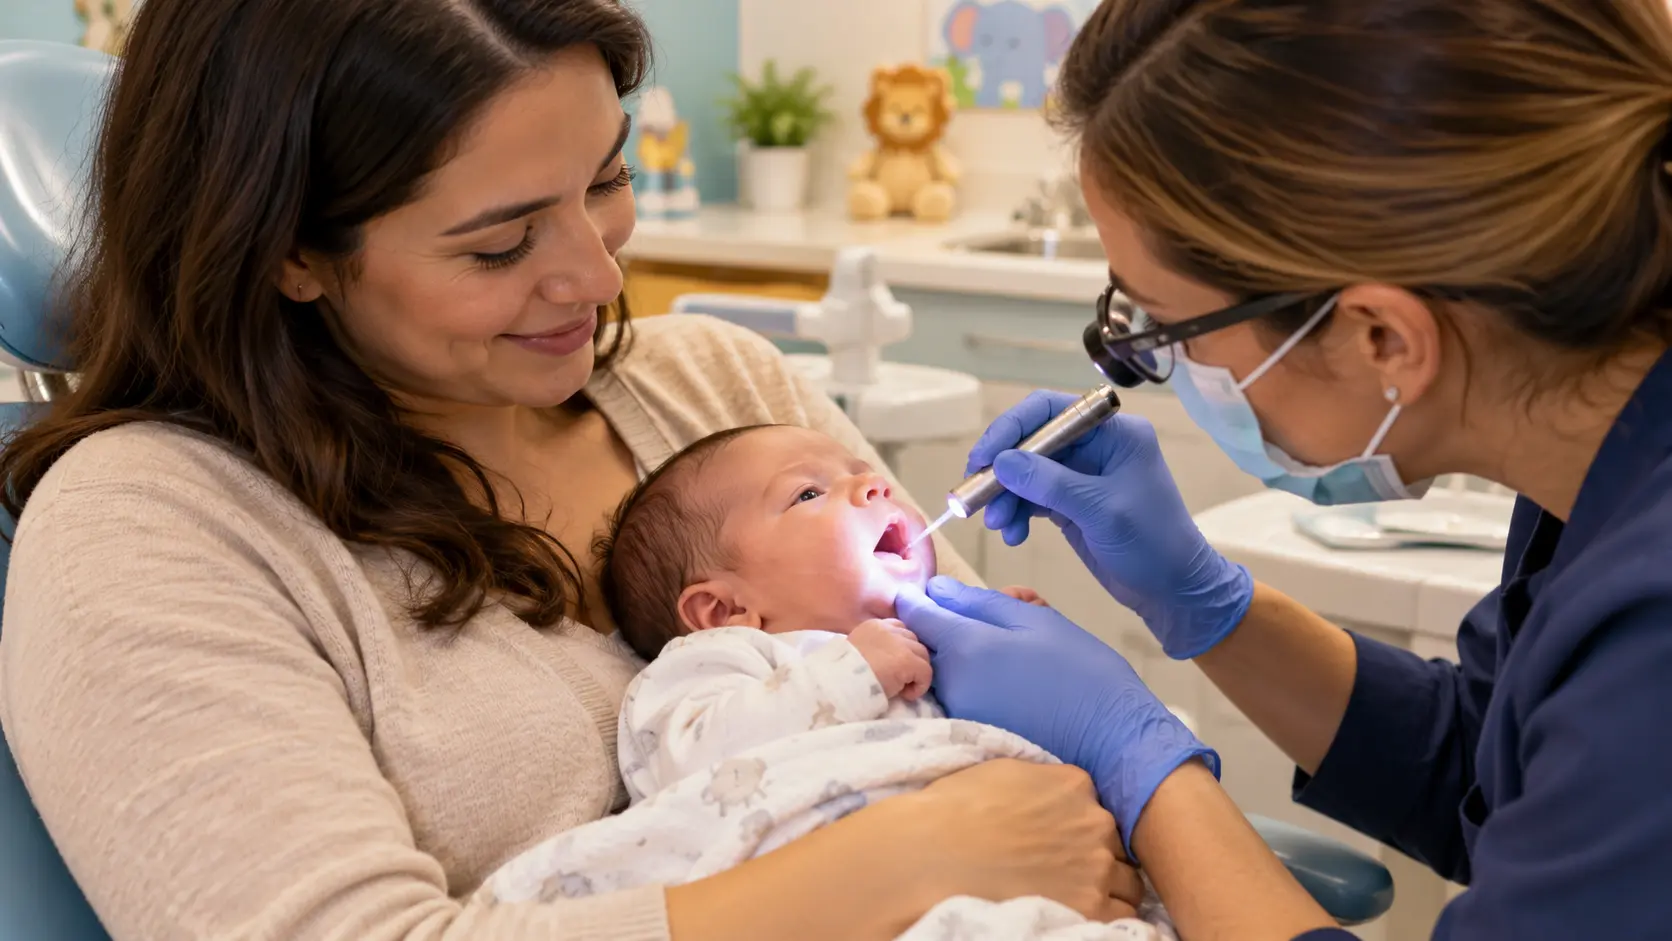

A baby born with one or more teeth has what dentists call natal teeth. They are uncommon, but they are not automatically dangerous or a sign that something is wrong. Most are normal baby teeth that come in early, usually in the front of the lower jaw. A pediatrician or pediatric dentist should check whether the tooth is stable, affects feeding, or rubs against the tongue. Stable, comfortable teeth can often remain; very loose or troublesome teeth may need treatment.
Key Takeaways
- Teeth already visible at birth are natal teeth; teeth that appear during the first 30 days are neonatal teeth.
- Most are normal primary teeth that erupted early. Only a small share are extra teeth.
- A natal tooth does not always need to be removed.
- Feeding trouble, tongue sores, bleeding or significant looseness deserves prompt evaluation.
- Do not pull, file or repeatedly wiggle the tooth at home.
What Are Natal Teeth?
Most babies begin getting teeth several months after birth, so spotting a tiny tooth during the newborn exam can be startling. Natal teeth simply arrive much earlier than expected.
The timing determines the name:
- Natal teeth are present when the baby is born.
- Neonatal teeth emerge during the first 30 days after birth.
This distinction helps with medical records, but parents’ concerns are much the same. The tooth needs to be checked for stability, position and its effect on feeding.
Natal and neonatal teeth are uncommon, although estimates vary considerably because studies define and count them differently. A 2023 systematic review and meta-analysis estimated that about 1 in 289 newborns has natal teeth, while noting important limitations in the available studies. They most often appear as one or two lower front teeth, the same teeth that usually come in first when regular teething begins. Most belong to the normal set of primary teeth and simply erupted early, although an occasional tooth is extra, or supernumerary. A dental examination, and sometimes an X-ray, can help tell the difference.
What Does a Natal Tooth Look Like?
A natal tooth may look like an ordinary small baby tooth, but many appear less developed. Parents may notice that it is:
- Smaller than expected
- Cone-shaped or narrow
- Yellowish, whitish or slightly brown
- Attached loosely to the gum
- Sharp along one edge
- Surrounded by mildly irritated gum tissue
Some have limited root development, which can make them more mobile than a tooth that erupts at the usual age. Others are surprisingly firm and cause no trouble at all.
Try not to test the tooth repeatedly with a finger. Frequent pushing can irritate the gum and does not reliably show whether the tooth is safe. Let your baby’s clinician or pediatric dentist assess its movement.
Why Is a Baby Born With Teeth?
In many cases, there is no single identifiable cause. The developing tooth may sit closer to the surface of the gum and erupt early. Family patterns have also been reported, and sometimes a parent or sibling had natal teeth too.
Natal teeth are occasionally associated with certain medical conditions, but most babies with a natal tooth do not have a syndrome or broader health problem. A tooth by itself is not a reason to assume that something went wrong during pregnancy. Your baby’s clinician will consider the whole newborn examination rather than treating the tooth as a diagnosis on its own.
Parents sometimes worry that medication, diet or something they did during pregnancy caused the early tooth. Current evidence does not support blaming everyday pregnancy choices. In most families, there was nothing that could have been predicted or prevented.
Does a Natal Tooth Need to Be Removed?
Not always. The first question is whether the tooth is causing a problem.
A firm natal tooth that does not interfere with feeding, injure the tongue or create another concern may only need observation. Preserving it can matter because it may be one of the baby’s normal primary teeth. Removing a normal primary tooth leaves that spot empty until the permanent tooth eventually arrives years later.
During an evaluation, the clinician may look at:
- How firmly the tooth is attached
- Whether it appears to be a normal primary tooth or an extra tooth
- Whether its edge is cutting the tongue or nearby tissue
- How the baby latches and transfers milk
- Whether the nursing parent has nipple pain or injury
- Whether there is bleeding, swelling or another oral finding
How Natal Teeth Can Affect Feeding
Many babies with natal teeth breastfeed or bottle-feed normally. The tongue usually covers the lower gum during sucking, so the presence of a lower tooth does not necessarily make nursing painful.
Trouble can arise when a sharp or poorly positioned edge rubs the underside of the baby’s tongue. Repeated friction may create a sore known as Riga-Fede disease. A baby with discomfort may pull away, cry during feeds, latch briefly and stop, or take less milk than usual. A nursing parent may also experience nipple soreness if the tooth contacts the breast.
If feeding becomes uncomfortable, do not assume you must stop breastfeeding. Ask your baby’s clinician or a qualified lactation professional to observe the latch, while a pediatric dentist evaluates the tooth itself. Sometimes feeding-position adjustments help. In other cases, a dentist may be able to smooth a sharp edge or cover it with a protective material. Treatment depends on the shape and stability of the tooth.
While you are working through feeding concerns, keep an eye on wet diapers and your baby’s alertness. A newborn who is taking noticeably less milk needs timely medical advice. Our guide to burping a baby can help with ordinary swallowed-air discomfort, but crying during feeds, repeated feed refusal or a visible mouth sore needs a more specific assessment.
When Removal May Be Recommended
Removal is not routine for every natal tooth. A pediatric dentist or pediatrician may consider it when:
- The tooth is so mobile that it may detach
- It repeatedly injures the tongue or other tissue
- Pain or injury is interfering with feeding
- Conservative treatment has not resolved the problem
- The tooth is extra and is unlikely to contribute to the normal primary dentition
- Its shape or position creates another clinical concern
The decision belongs with a qualified clinician. Newborn procedures require attention to bleeding risk, the baby’s medical history and whether routine vitamin K was given after birth. Parents should never try to remove the tooth themselves, even if it looks barely attached.
If removal is advised, ask whether the tooth is believed to be a normal primary tooth or an extra one, what comfort measures will be used and what feeding should look like afterward. Follow-up may be recommended to check that the gum heals and feeding improves.
What Parents Can Do at Home
Until your baby is evaluated, keep care simple and gentle.
Leave the Tooth Alone
Do not pull it, twist it, file its edge or tie anything around it. These actions can cause pain, bleeding, infection or an unsafe detachment.
Continue Feeding If Your Baby Is Comfortable
A visible tooth alone is not a reason to delay breastfeeding or bottle-feeding. Watch the baby rather than the clock: steady sucking, audible swallowing and relaxed behavior are reassuring signs.
Look Under the Tongue Once a Day
With clean hands and good light, briefly check for a red spot, cut or ulcer. Avoid repeatedly lifting or pressing the tongue when your baby is upset.
Watch for Changes Instead of Testing Movement
If the tooth suddenly seems more angled, appears longer or moves visibly during feeding, call your baby’s clinician.
Follow Professional Cleaning Advice
A pediatric dentist can show you how to keep the area clean without irritating delicate newborn tissue. Do not apply numbing gels, clove oil or other home remedies to a newborn’s mouth unless a clinician specifically directs you to do so.
When to Call the Pediatrician or Pediatric Dentist
Arrange an assessment soon after a natal tooth is found, even if your baby seems comfortable. Contact the clinician right away if:
- The tooth is visibly loose or becoming looser
- Your baby struggles to latch, repeatedly refuses feeds or takes much less milk than usual
- There is a cut, ulcer or persistent red area under the tongue
- The gum is swollen, bleeding or draining fluid
- The tooth is rubbing or injuring the nursing parent
- Your baby appears unusually sleepy or has fewer wet diapers
Seek urgent medical help if the tooth suddenly disappears and your baby is coughing, choking, wheezing, having trouble breathing or turning blue. Breathing symptoms raise concern that it may have entered the airway. If the tooth is missing but your baby is breathing normally, call the pediatrician promptly for advice.
What Happens to Teething Afterward?
Having a natal tooth does not mean all of your baby’s teeth will arrive early. The rest of the primary teeth may follow a more typical schedule.
If the natal tooth is retained, the dentist may monitor its enamel, position and stability as your baby grows. Early-erupted teeth can have thinner or less-developed enamel, so preventive care matters. The American Academy of Pediatric Dentistry recommends establishing a dental home no later than a child’s first birthday, and a baby with a natal tooth may need dental care much sooner.
If a normal primary tooth is removed, another baby tooth does not grow in to replace it. The pediatric dentist can monitor spacing and development over time. If the removed tooth was supernumerary, the normal primary tooth may still erupt later.
A Reassuring Perspective
Seeing a tooth in your newborn’s mouth can make an already intense first week feel even more uncertain. In most cases, the next step is simply a careful examination. Many stable natal teeth can be watched, and when a tooth does cause feeding trouble or injury, pediatric clinicians have conservative and surgical options.
Focus on three things: whether your baby can feed comfortably, whether the tongue and gums look healthy and whether the tooth remains stable. Arrange an early professional assessment, avoid home treatment and let the examination guide what happens next.
This article provides general educational information and is not a substitute for care from your baby’s pediatrician or pediatric dentist.
